


Featured Resources
-
STORM Therapeutics: From Lead to Pre-Candidate Nomination in 18 Months

STORM Therapeutics: From Lead to Pre-Candidate Nomination in 18 Months
Case study




Discover precise insights into brain neurochemistry with Sygnature Discovery's in vivo microdialysis and cOFM services. With over 20 years of expertise, we design bespoke studies that reveal how compounds modulate neurotransmitter systems in health and disease. Using UHPLC/HPLC with electrochemical detection or mass spectrometry, we deliver robust PK/PD data to support confident CNS decision making.


July 30, 2015

Inobrodib, an exciting, first-in-class oral anti-cancer drug in clinical development by CellCentric, was collaboratively designed, synthesised and supported on its pre-clinical journey by an integrated project team at Sygnature Discovery. Inobrodib is now showing promising results in Phase I and II trials for multiple myeloma and other cancer types.

In drug discovery, generating targets is no longer the challenge. The real question is how to identify the few worth investing months of research and significant resources to pursue. Hear expert perspectives on how AI, pathway analysis and scientific expertise are shaping modern target identification.
July 7, 2026

Stay up to date with the latest company updates, milestones, and announcements.

Explore upcoming conferences and scientific meetings where you can connect with our team.

At Sygnature Discovery, we deliver world-leading drug discovery solutions to accelerate your compound from idea to clinic.

Our leadership team brings diverse experience and insight, driving collaboration and innovation across drug discovery.

Explore careers at Sygnature Discovery and join a global team committed to science, collaboration, and integrity.
Inobrodib, an exciting, first-in-class oral anti-cancer drug in clinical development by CellCentric, was collaboratively designed, synthesised and supported on its pre-clinical journey by an integrated project team at Sygnature Discovery. Inobrodib is now showing promising results in Phase I and II trials for multiple myeloma and other cancer types.
At Sygnature Discovery, we deliver world-leading drug discovery solutions to accelerate your compound from idea to clinic.
Our leadership team brings diverse experience and insight, driving collaboration and innovation across drug discovery.
Explore careers at Sygnature Discovery and join a global team committed to science, collaboration, and integrity.
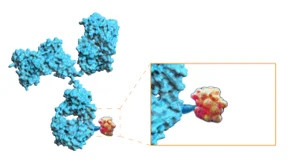
Antibody-drug conjugates (ADCs) were originally developed for cancer treatment: an antibody that binds a tumor-specific protein is chemically linked to a toxic drug (payload) with the drug delivered to cancer cells while sparing healthy tissue. “Anti-inflammatory ADCs” apply that same targeting logic to autoimmune and inflammatory diseases, swapping the cytotoxic payload for an anti-inflammatory or immunosuppressive drug and using the antibody to steer it to the disease-relevant tissue.
For twenty years, antibody-drug conjugates were oncology’s story to tell. Strap a vicious payload to a homing antibody, let the antibody find the tumor cell, and let the payload do what it could never safely do on its own — kill selectively, at a dose that would otherwise be intolerable. Nineteen ADCs are now approved for cancer treatment, and the field has become one of the most productive corners of drug development. What’s less discussed outside specialist circles, is that the same trick is now being pointed at inflammation instead of malignancy — and it may end up mattering more to more patients, if we get it right.
As an example of why we need anti-inflammatory ADCs, glucocorticoid receptor modulators (GRMs or glucocorticosteroids) are, on paper, one of the best anti-inflammatory medicines ever produced: cheap, fast-acting, and effective across an enormous range of autoimmune and inflammatory conditions. In practice they are very effective in the short term but for chronic conditions, they are also one of the most self-limiting, because the same broad receptor activation that calms an inflamed joint also thins bone, raises blood sugar, disrupts sleep, and suppresses the adrenal axis when used at the doses and durations most diseases actually require. Rheumatologists had spent decades prescribing a drug they know is doing damage, because the alternative — undertreated disease — is worse. That’s not a minor inefficiency in modern medicine; it’s a genuine, decades-old failure to separate a drug’s desired effect from its price.
With the advent of biologics, essentially proteins (usually a monoclonal antibody or an engineered derivative) designed to bind to and inhibit inflammation targets formally untreatable with smaller drugs, a huge leap forward was taken on the road to effectively treating numerous inflammatory diseases and syndromes. Biologics however come with their own baggage, huge cost of production hence a steep price for the consumer, storage conditions precluding easy use anywhere without a fridge (rather selective for the so-called first world) parenteral administration (not good if you don’t want to use a needle to self-administer), truly enormous dosages to achieve efficacy (often leading to the ever-vigilant body reacting to the high levels of an essentially foreign protein).
Anti-inflammatory ADCs are a direct attempt to work with advantages of both modalities, the selectivity of a biologics and the efficacy/potency of the smaller drugs like a GRM. In this case the aim is to (hopefully drastically) reduce the amount of both used (avoiding “off target” effects) but maintain the effect by very selective targeting.
So, what’s out there? It’s probably best to categorize the most recent efforts based on how close they are to treating those who need them, there are no shortage of candidates for development, some very mature others very early stage but the closest was Abbvie and ABBV-3373 (see below).
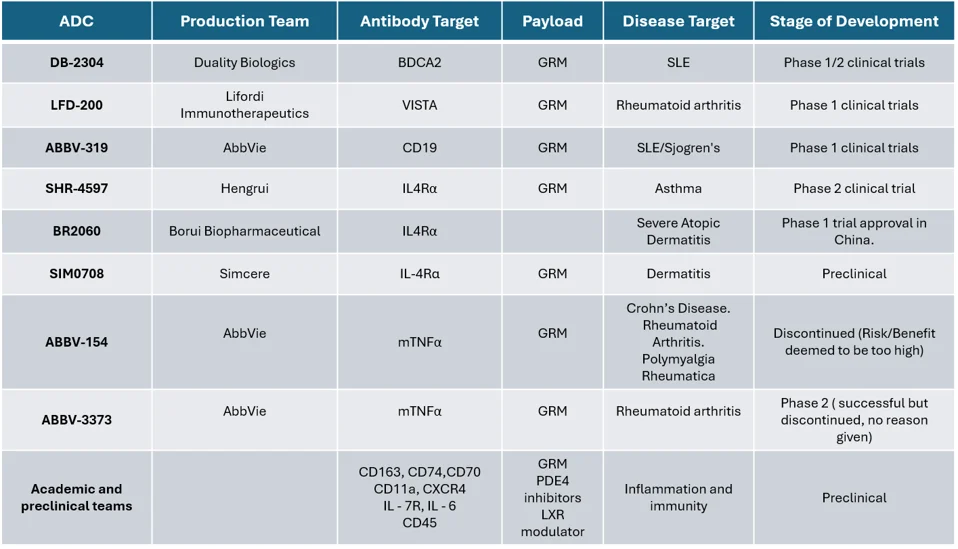
AbbVie’s ABBV-3373 paired adalimumab — a conventional anti-TNF antibody — with a glucocorticoid receptor modulator, delivering the steroid payload specifically into TNF-engaged immune cells rather than systemically. In a Phase 2 rheumatoid arthritis trial, it outperformed adalimumab alone on disease activity scores while producing meaningfully fewer adverse events, and early studies found no detectable suppression of serum cortisol at therapeutic doses — the classic marker of systemic steroid toxicity. Please notice the past tense at the beginning of this paragraph. Abbvie took these results and, for their own reasons, discontinued the development of ABBV-3373. There are many possible reasons why this happened (it doesn’t look like a toxicity issue, phase-1 trials were very well executed with few or no issues) and I would not want to second guess such a complex business vs science issue . What is encouraging is that Abbvie took the very clever route (functionality in both the Oncology and Inflammation space) of continuing to develop ABBV-319. It isn’t alone. Lifordi Immunotherapeutics presented Phase 1 data this June on LFD-200, a subcutaneous glucocorticoid ADC showing dose-responsive anti-inflammatory activity with no cortisol impact, dosing in RA patients is now underway.
None of the commitment and innovation demonstrated above makes this a sure thing, the field would benefit from resisting the “next ADC gold rush” framing that oncology occasionally slid into.
First, the safety margin that makes ADCs elegant in cancer — killing a tumor cell is the goal, so some off-target death is tolerated — doesn’t exist here. An anti-inflammatory ADC’s entire value proposition rests on not suppressing the immune system anywhere it shouldn’t, which is a much higher bar for a linker-payload system to clear reliably across a diverse patient population.
Second, chronic dosing changes the risk calculus. Cancer ADCs are typically given for a defined, often short, course. Autoimmune disease is a decades-long condition, and antibody-based therapies carry immunogenicity risk that compounds with years of repeated dosing in a way a twelve-week oncology regimen doesn’t have to reckon with.
Third, the comparison set is unforgiving. Anti-inflammatory ADCs aren’t just competing against oral steroids; they’re competing against JAK inhibitors, IL-17 and IL-23 blockers, and an increasingly crowded field of targeted oral and biologic therapies. An ADC has to be meaningfully better than “another biologic,” not just better than prednisone, to earn its almost-certainly higher manufacturing cost and price tag.
And regulators are watching the category closely at exactly the moment it’s trying to scale: the FDA’s 2026 draft guidance is pushing conjugated products toward more analytical characterization and less reliance on animal toxicology, which is the right scientific direction but adds real complexity for developers working with novel, less-platformed linker chemistries rather than the well-trodden oncology playbook.
So far in this article we have focused on ADCs with diverse antibody targeting but from casual observation there is a strong bias towards GRM payloads, with these drugs and their decedents in their 80’s perhaps the “new” kids on the block should be given a chance so perhaps co-opt them rather than compete with them. If you want to make a regulators (and accountants) hair stand on end, there are numerous targets that were off-limits 20 years ago from RAS to SH2 domain possessing proteins with a truly impressive array of drug modalities including PROTAC, glue-degraders, RIPTACs, Bispecifc-antibodies, siRNAs, CRISPR/Cas9 and RNA based vaccines to consider.
This is one of the more genuinely promising ideas in inflammatory disease right now, not because it’s novel biology — targeted delivery is an old concept — but because the early human data on ABBV-3373 and LFD-200 are doing what mouse models alone never do: showing efficacy and a spared high dose payload risk in real patients. That’s rare enough in this field to take seriously.
But “promising” is doing a lot of work in that sentence, and the technology is still one or two Phase 3 readouts away from proving it can do in a diverse RA or lupus population what it’s done in tightly controlled early trials. The right posture is cautious optimism: root for the mechanism, watch the immunogenicity data closely as dosing durations lengthen, and don’t let a handful of strong Phase 1/2 results get mistaken for a solved problem. Oncology’s ADC story took two decades and several public failures before it became a genuine success story. Immunology should expect, and plan for, the same arc — just hopefully with a shorter learning curve.


Peak Proteins, NuChem Sciences, and SB Drug Discovery have now fully integrated with Sygnature Discovery.